Quick answer
Gastric Sleeve vs Gastric Bypass: Pros, Cons and Long-Term Differences: the right answer depends on diagnosis, the actual treatment plan and individual risk factors. Use this article to prepare for consultation, then have the treating clinic confirm timing, medicines, suitability and travel planning for your case.
- Do not confirm treatment before adequate clinical assessment.
- Get scope, risks, aftercare and return-travel criteria in writing.
- For care in Turkey, verify the authorised facility and responsible clinician.
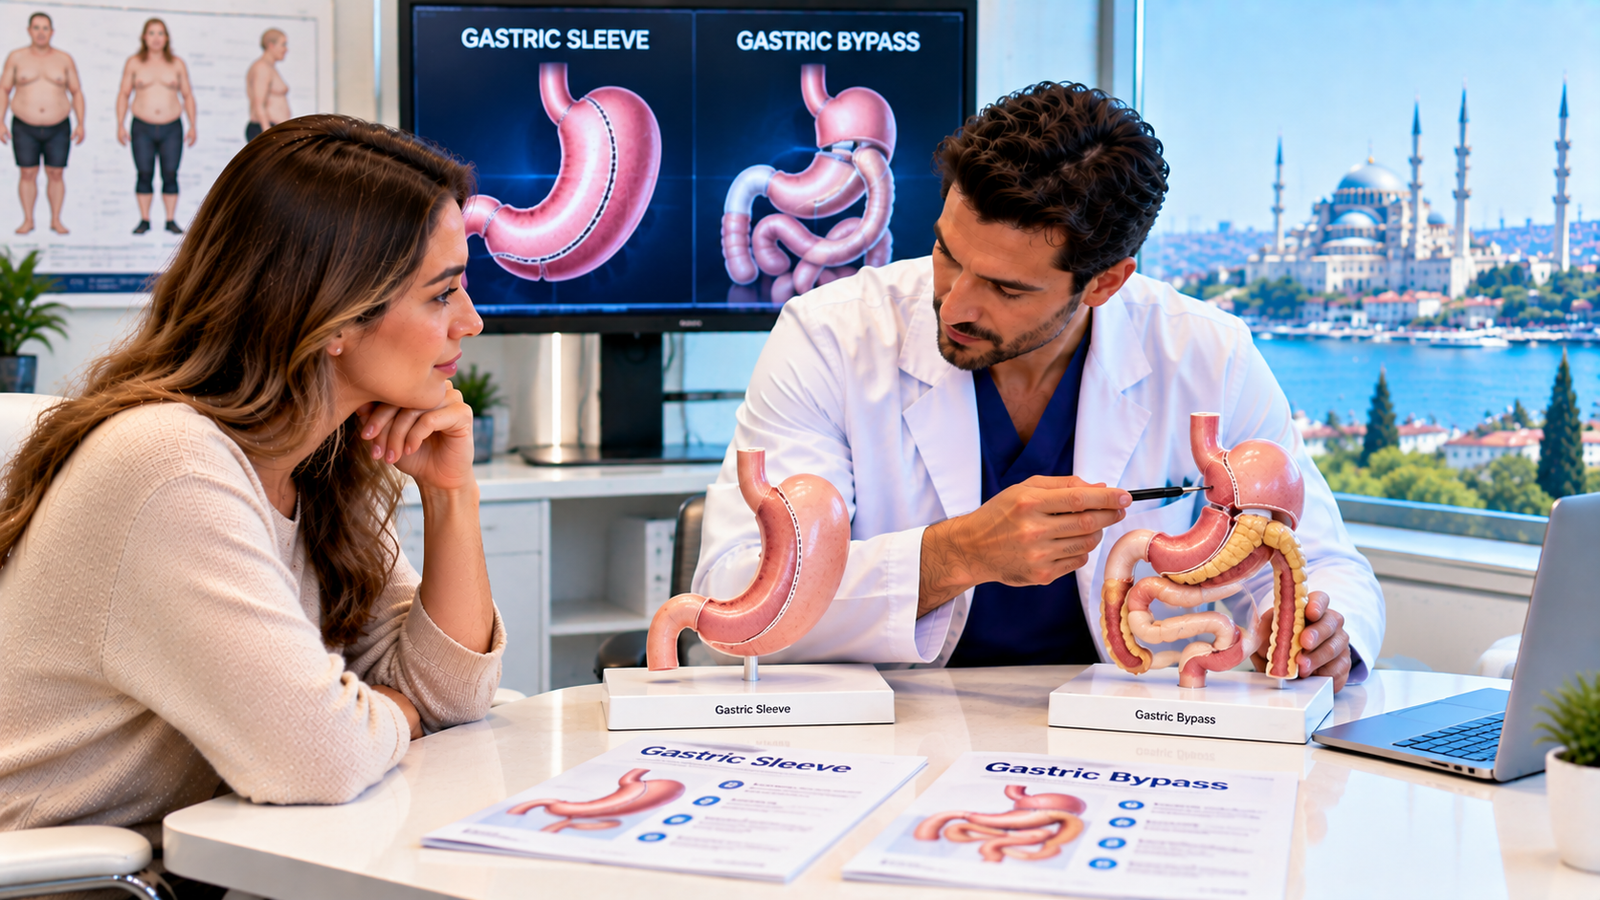
Gastric sleeve vs gastric bypass is a comparison between two established metabolic and bariatric operations that change the stomach in different ways. Sleeve gastrectomy removes most of the stomach and leaves a narrow gastric sleeve without rerouting the intestine. Roux-en-Y gastric bypass creates a small gastric pouch and reroutes part of the small intestine. Long-term randomised-trial reviews show that both can produce substantial weight loss and metabolic benefit, but bypass often has an advantage for reflux control and may produce somewhat greater long-term weight loss, while sleeve has simpler anatomy and fewer late major complications in some analyses. Start with our Roux-en-Y Gastric Bypass page and let the bariatric team choose according to your health profile rather than a single headline comparison.
What Sleeve Gastrectomy Changes
Sleeve gastrectomy removes a large part of the stomach and creates a narrow tube-shaped stomach. Food still follows the normal intestinal route. The operation reduces stomach capacity and changes appetite-related hormones, but it does not create an intestinal bypass.
What Roux-en-Y Gastric Bypass Changes
Roux-en-Y gastric bypass creates a small stomach pouch and connects it to a lower part of the small intestine, bypassing the remaining stomach and the first part of the small bowel. This creates both restriction and metabolic effects and changes how some nutrients and medicines are absorbed.
Which Produces More Weight Loss?
A 2025 systematic review and meta-analysis of 9 randomised trials involving 1,489 patients found greater long-term excess-weight loss and total-weight loss after gastric bypass than after sleeve gastrectomy. Other very long-term reviews suggest the difference can become smaller by around 10 years.
The practical message is that both operations can be effective, but bypass may provide a larger average weight-loss effect in some populations. Individual results still vary widely.
Which Is Better For Type 2 Diabetes?
Both procedures can improve type 2 diabetes through weight loss and metabolic changes. The 2025 randomised-trial meta-analysis found higher diabetes remission after gastric bypass, although other long-term analyses have found smaller or non-significant differences at later follow-up.
Diabetes duration, insulin use, pancreatic function, body mass index and other health factors matter when the surgeon estimates expected metabolic benefit.
Reflux Is One Of The Biggest Differences
Gastric sleeve can cause new reflux or worsen existing gastro-oesophageal reflux in some patients. Roux-en-Y gastric bypass generally improves reflux more reliably and is often considered when significant reflux is already present.
A patient with severe reflux, oesophagitis or Barrett’s oesophagus needs a careful upper-gastrointestinal assessment before a sleeve is chosen.
Which Operation Has More Nutritional Consequences?
Both operations require long-term vitamin and mineral supplementation and blood-test monitoring. Gastric bypass usually creates greater risk of deficiencies because food bypasses part of the small intestine and absorption of nutrients such as iron, vitamin B12, calcium and vitamin D can be reduced.
Sleeve gastrectomy can also lead to deficiencies because intake is reduced and food tolerance changes, so it should not be described as nutritionally consequence-free.
Medication Absorption Can Change More After Bypass
Rerouting the intestine can change the absorption of some medicines after gastric bypass. Slow-release, enteric-coated or drugs with narrow therapeutic ranges may need special review.
Sleeve gastrectomy can also alter absorption through changes in stomach size, acidity and emptying, but the effect is generally less anatomically complex than after bypass.
Dumping Syndrome Is More Associated With Bypass
Rapid delivery of concentrated food into the small intestine after gastric bypass can cause dumping symptoms such as abdominal discomfort, diarrhoea, palpitations, sweating or weakness. Dietary behaviour is an important part of prevention and management.
Dumping can occur after other gastric operations but is more classically associated with gastric bypass.
What Are The Main Surgical Risks?
Both operations can cause bleeding, infection, leak, blood clots and anaesthetic complications. Sleeve-specific long-term concerns include reflux and, in some patients, later conversion to bypass. Bypass-specific concerns include marginal ulcers, internal hernia, narrowing at the connection and nutritional deficiency.
The actual risk depends on the patient, surgeon, hospital, previous surgery and long-term follow-up.
Does Sleeve Have A Simpler Recovery?
Sleeve gastrectomy has no intestinal rerouting, so the anatomy is simpler and the operation is usually technically less complex than Roux-en-Y bypass. That does not mean recovery is trivial or that the operation is safer for every patient.
Both require hospital monitoring, staged diet progression, hydration, early walking, thrombosis prevention and long-term bariatric follow-up.
Who May Be More Suited To Gastric Bypass?
- Selected patients with significant gastro-oesophageal reflux.
- Some patients in whom stronger metabolic effect for type 2 diabetes is a major goal.
- Patients whose surgeon expects bypass to offer a better balance of weight-loss and reflux outcomes.
- People who understand and can follow lifelong supplementation and monitoring requirements.
Who May Be More Suited To Sleeve Gastrectomy?
- Selected patients who do not have a strong reflux-related reason to prefer bypass.
- People for whom avoiding intestinal rerouting is clinically useful.
- Patients whose medical history or anatomy makes sleeve the more appropriate operation.
- People who understand that sleeve still requires lifelong nutritional and weight follow-up.
Questions To Ask Before Choosing
- How do my reflux symptoms affect the choice?
- Which operation better fits my diabetes history and metabolic goals?
- What long-term weight-loss difference do you expect in my case?
- How do my current medicines affect the decision?
- What vitamin and mineral supplements will I need?
- What blood tests are required long term?
- What late complications are most relevant to me?
- Could a sleeve later need conversion to bypass?
- How will follow-up continue after I return home?
How Turkelite Medcare Coordinates Bariatric Planning
Turkelite Medcare is a patient coordination service, not the treating bariatric unit. We do not choose sleeve or bypass, estimate individual surgical risk or manage long-term nutritional prescriptions.
Our role is to organise provider questions, records, appointments, travel and the return-home handover around the plan confirmed by the bariatric team. See patient services.
Frequently Asked Questions
Is Gastric Bypass Better Than Gastric Sleeve?
Not for everyone. Bypass may offer stronger reflux control and somewhat greater average long-term weight loss in some studies, while sleeve has simpler anatomy and can have fewer late major complications.
Which Is Better For Reflux?
Roux-en-Y gastric bypass generally has the stronger evidence for reflux improvement. Sleeve can worsen or cause reflux in some patients.
Which Has More Vitamin Deficiency Risk?
Both need supplementation and monitoring, but gastric bypass usually has the greater malabsorption-related deficiency risk.
Can A Sleeve Be Converted To A Bypass?
Yes, selected patients may undergo conversion later, especially for severe reflux, inadequate weight response or another complication, but revisional surgery carries its own risks.
The Right Operation Depends On The Problem You Need To Solve
The useful comparison is not a universal list of winners and losers. It is whether reflux, diabetes, weight history, medicines, nutritional risk, previous surgery and long-term follow-up make sleeve gastrectomy or Roux-en-Y gastric bypass the more appropriate operation for the individual patient.
Sources and further reading
- NHS: What is weight loss surgery?
- NHS: Overweight and obesity in adults
- Republic of Türkiye Ministry of Health: International health tourism regulation
These sources support general patient information. Individual medical recommendations must come from the treating clinician.
View the related treatment area
This content is for general information and does not replace individual medical advice, diagnosis or treatment. Discuss treatment suitability, risks and recovery with a qualified healthcare professional.