Quick answer
Sleep Apnea Surgery in Turkey: Selection, Options & Follow-Up: the right answer depends on diagnosis, the actual treatment plan and individual risk factors. Use this article to prepare for consultation, then have the treating clinic confirm timing, medicines, suitability and travel planning for your case.
- Do not confirm treatment before adequate clinical assessment.
- Get scope, risks, aftercare and return-travel criteria in writing.
- For care in Turkey, verify the authorised facility and responsible clinician.
Sleep apnea surgery in Turkey is not one operation and it is not the first treatment for every person with obstructive sleep apnea. The correct pathway starts with a confirmed sleep-apnea diagnosis, the severity of the condition, symptoms, body weight, previous treatment and the exact site of airway collapse. The American Academy of Sleep Medicine recommends discussion of referral to a sleep surgeon for adults with obstructive sleep apnea who cannot tolerate or accept positive-airway-pressure treatment and have a body mass index below 40. The same guideline says referral for bariatric-surgery discussion should be considered when body mass index is 35 or above, with both referrals potentially relevant between 35 and 40. Start with our Sleep Apnea Surgery page and make sure the operation is linked to an identified anatomical problem rather than chosen from a package.
Sleep Apnea Surgery Is A Category, Not One Procedure
Obstructive sleep apnea happens when the upper airway repeatedly narrows or closes during sleep. Surgery can target different parts of that airway, so two people with the same sleep-study diagnosis may need completely different treatment plans.
Possible surgical targets include enlarged tonsils, the soft palate and throat walls, the tongue base, the jaw skeleton or selected nerve-control pathways. Nasal surgery can also improve nasal airflow, but professional guidance notes that its effect on the apnea-hypopnea index is often modest when used alone.
Positive-Airway-Pressure Treatment Is Still The Initial Treatment For Many Adults
Professional sleep and ear-nose-throat guidance continues to place positive-airway-pressure treatment as an initial option for many adults, especially with moderate to severe obstructive sleep apnea. Surgery is commonly discussed when that treatment is not tolerated, is not accepted, does not adequately control the condition or when a correctable anatomical obstruction is identified.
A surgical consultation should therefore review what non-surgical treatment has already been tried and why it was unsuccessful or unsuitable.
What Tests Should Be Clear Before Surgery?
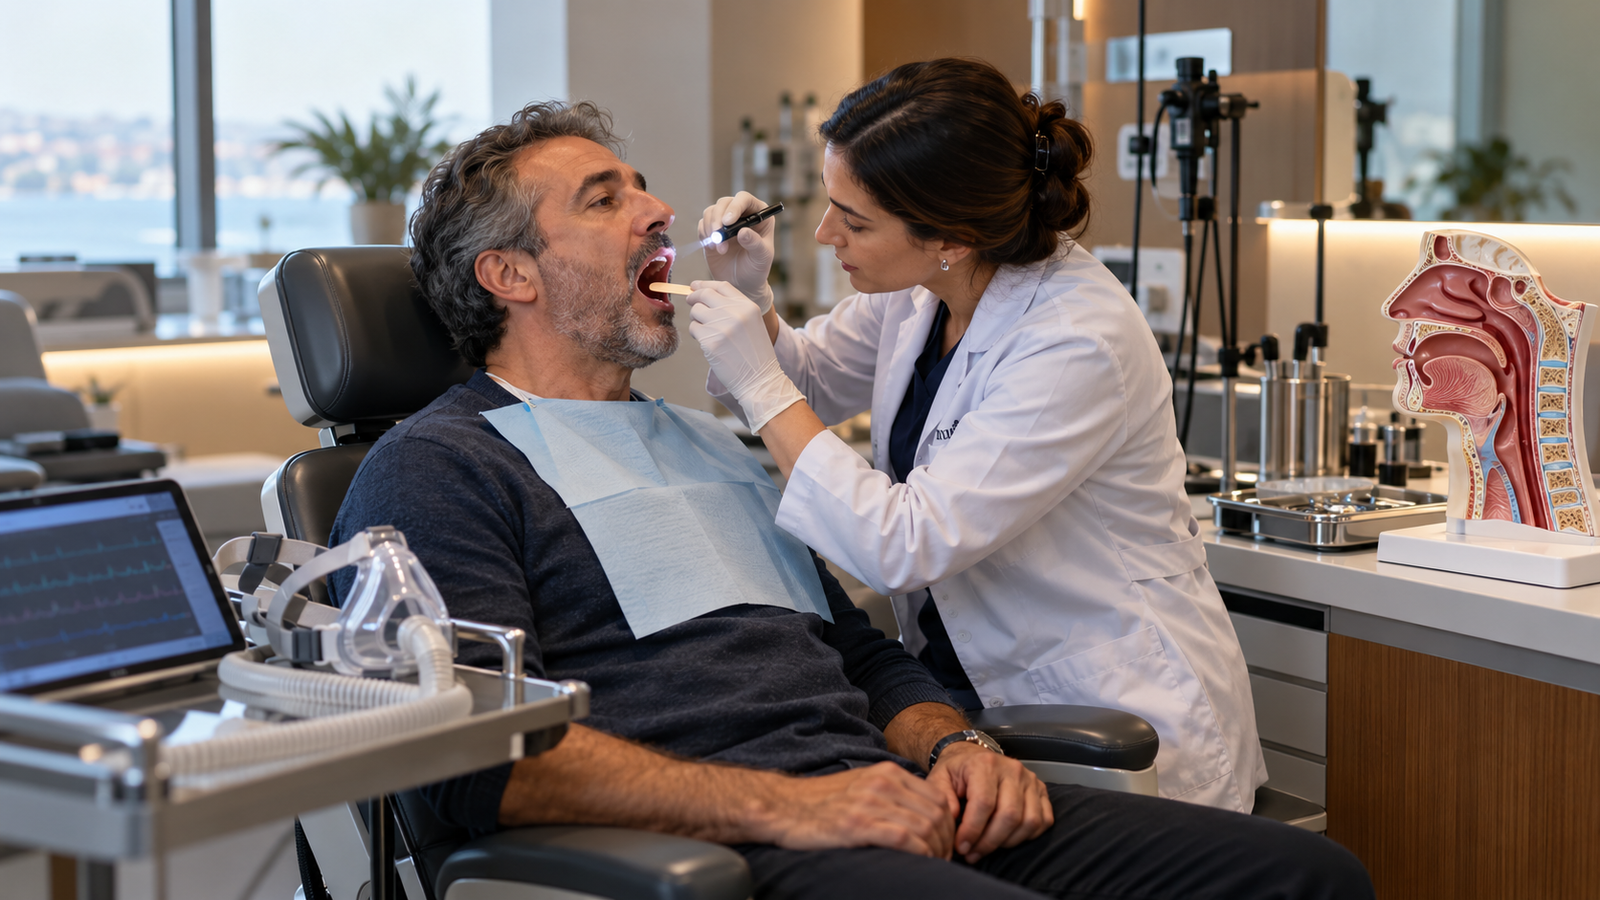
The diagnosis should be supported by an appropriate sleep study. The surgical team may also use examination of the nose, mouth, palate and throat, imaging when needed and, in selected cases, sleep endoscopy performed under medication to observe where the airway collapses during sleep-like conditions.
Those findings should connect directly to the proposed operation. Ask the surgeon which finding the procedure is intended to correct.
What Operations May Be Considered?
- Tonsil removal when enlarged tonsils are a major obstructive factor.
- Palatal or throat surgery intended to enlarge or stabilise the airway.
- Tongue-base procedures when obstruction occurs lower in the throat.
- Upper- and lower-jaw advancement in selected skeletal patterns.
- Stimulation of the nerve controlling tongue movement in carefully selected patients.
- Nasal surgery as an adjunct when nasal obstruction contributes to symptoms or difficulty using positive-airway-pressure treatment.
Why Anatomy Matters More Than The Name Of The Operation
Surgery works best when the operation matches the level and pattern of obstruction. A palate procedure will not correct every tongue-base problem, and nasal surgery alone may not treat collapse lower in the airway.
This is why a credible plan should describe the site of obstruction, the intended functional change and the reason that procedure was selected over alternatives.
Can Sleep Apnea Surgery Cure The Condition?
It can substantially improve obstructive sleep apnea in selected patients, but no operation should be presented as a guaranteed cure. Some people have residual apnea after surgery and may still need positive-airway-pressure treatment, an oral appliance, weight management or another procedure.
A follow-up sleep study or other objective reassessment is important because feeling better does not prove that breathing events during sleep have fully resolved.
What Does The Evidence Say About Surgical Selection?
The American Academy of Sleep Medicine guideline focuses on when adults should be referred for surgical consultation rather than claiming that one airway operation is best for everyone. It recommends discussing sleep-surgeon referral when positive-airway-pressure treatment is not tolerated or accepted and body mass index is below 40.
Ear-nose-throat guidance also recognises procedures such as tonsil surgery, palate surgery, tongue-base surgery, jaw advancement and tongue-nerve stimulation for selected patients. The useful question is therefore not “Which surgery has the highest success rate?” but “Which anatomical target is causing my obstruction, and how will success be measured in my case?”
How Should Success Be Measured?
Success should not be measured only by snoring. Important outcomes include the apnea-hypopnea index, oxygen levels, daytime sleepiness, sleep quality, blood-pressure risk, quality of life and whether other therapy is still needed.
Ask in advance what postoperative test will be used and when the treating team plans to repeat it.
What Are The Main Surgical Risks?
Risks depend on the procedure. They can include bleeding, infection, pain, swallowing difficulty, voice or taste changes, airway swelling, dental or nerve problems with some operations and the possibility that apnea improves less than expected.
The consent discussion should be procedure-specific. A generic list for “sleep apnea surgery” is not enough when the planned operation involves a particular palate, tongue, jaw or implanted device procedure.
How Long Should You Stay In Turkey?
There is no universal stay length because recovery differs widely between a tonsil operation, palate surgery, jaw advancement and an implanted stimulation device. The treating surgeon should define hospital observation, early review, wound checks, diet progression and the minimum recovery milestones before air travel.
Do not book a fixed return flight until the exact operation and early postoperative review schedule are confirmed.
What Should Be Checked Before Flying Home?
You should be able to maintain hydration, control pain with the planned medicines, breathe safely, manage the recommended diet and know how to respond to bleeding, fever, increasing swelling or breathing difficulty.
Airway or bleeding symptoms can be urgent after some sleep-apnea operations. Seek local emergency care rather than waiting for an overseas message if breathing becomes difficult or bleeding is significant.
Questions To Ask The Sleep Surgeon
- What type and severity of sleep apnea do I have?
- What exact level of my airway is collapsing?
- Why is surgery being considered instead of continued non-surgical treatment?
- Which operation or combination of operations is planned?
- How will success be measured after surgery?
- Will I need another sleep study?
- Could I still need positive-airway-pressure treatment afterwards?
- What complications are specific to this operation?
- How long should I remain near the treating hospital before flying?
- Who reviews me after I return home?
How Turkelite Medcare Coordinates Sleep-Apnea Surgery
Turkelite Medcare is a patient coordination service, not the treating sleep clinic or surgical team. We do not diagnose sleep apnea, choose the operation or decide whether a patient can stop positive-airway-pressure treatment.
Our role is to organise provider questions, requested records, appointments, travel, accommodation and the return-home handover around the clinical plan confirmed by the treating team. See patient services.
Frequently Asked Questions
Is Sleep Apnea Surgery A Replacement For Positive-Airway-Pressure Treatment?
Not automatically. Surgery is considered in selected patients, especially when positive-airway-pressure treatment is not tolerated or an anatomical obstruction can be targeted.
Is There One Best Sleep Apnea Operation?
No. The appropriate operation depends on where and how the airway collapses, the severity of apnea, body weight, anatomy and previous treatment.
Can Sleep Apnea Come Back After Surgery?
Yes. Residual or recurrent obstruction can occur, especially if anatomy, body weight or the underlying condition changes. Objective follow-up remains important.
Can I Fly Soon After Sleep Apnea Surgery?
The timing depends on the exact operation and early recovery. The treating surgeon should confirm when bleeding, airway, hydration and pain risks are controlled enough for travel.
The Operation Should Follow The Sleep Diagnosis And The Airway Anatomy
Sleep-apnea surgery is most useful when the diagnosis is confirmed, the obstruction is mapped and the proposed operation has a clear anatomical purpose. Medical decision first; travel second.
Sources and further reading
- NHS: Hearing aids and implants
- CUH: Tonsillectomy
- Republic of Türkiye Ministry of Health: International health tourism regulation
These sources support general patient information. Individual medical recommendations must come from the treating clinician.
View the related treatment area
This content is for general information and does not replace individual medical advice, diagnosis or treatment. Discuss treatment suitability, risks and recovery with a qualified healthcare professional.